- 原文:15 September 2026: Image Quiz #195 / Granular cell tumor。
- 作者:Salvatore Luceno, M.D., M.Sc.;Anna Biernacka, M.D., Ph.D.。
- 博客发布及专题编辑部最后更新 2026-09-15。
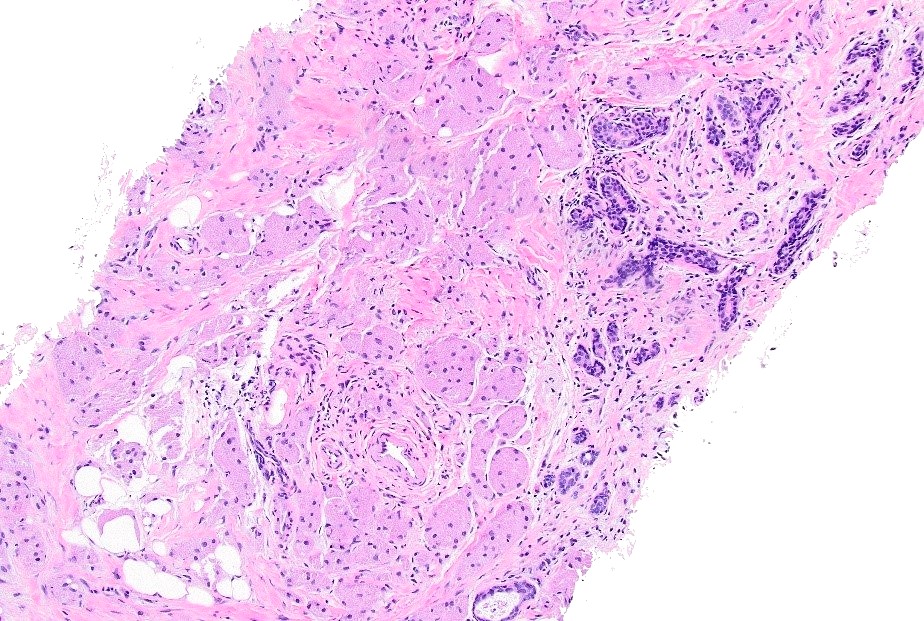
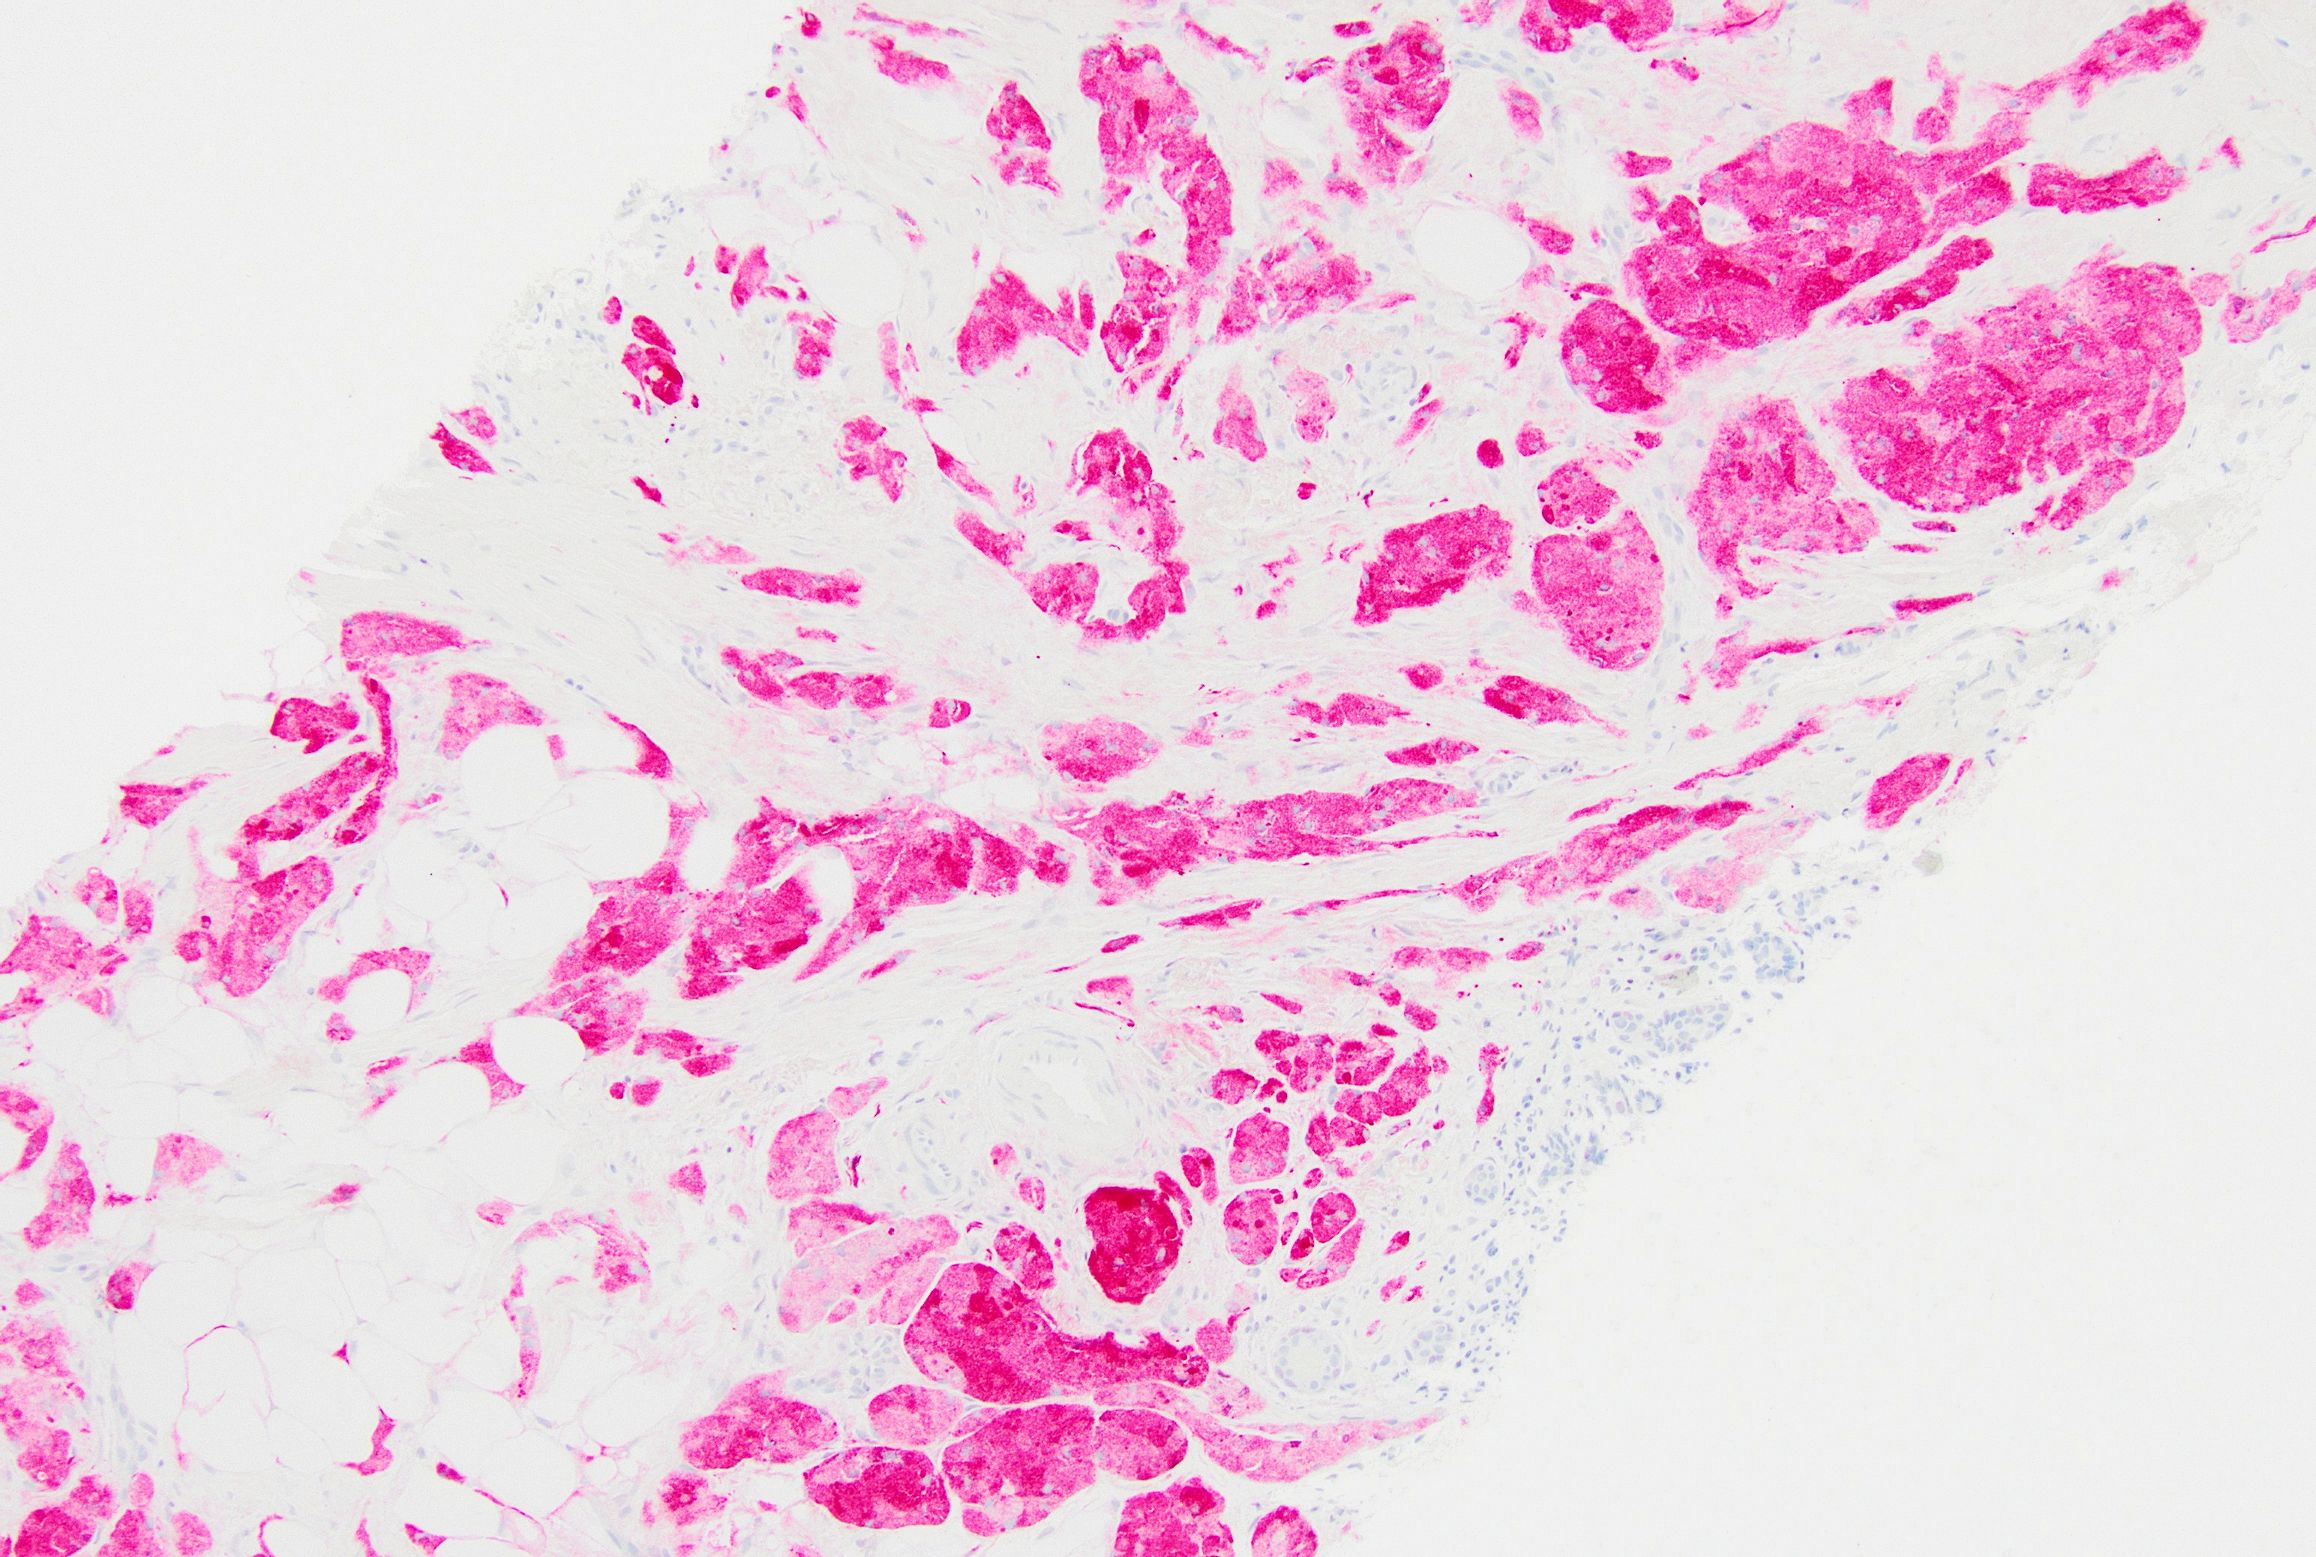
一名 45 岁患者,影像显示 1.5 cm、边界不清且无钙化的乳腺肿块。取材后的 H&E 切片如图。病变细胞 S100 强、弥漫阳性。下列哪项是最佳诊断?
请选择答案:
- 大汗腺化生
- 非典型导管增生
- 颗粒细胞瘤
- 浸润性导管癌
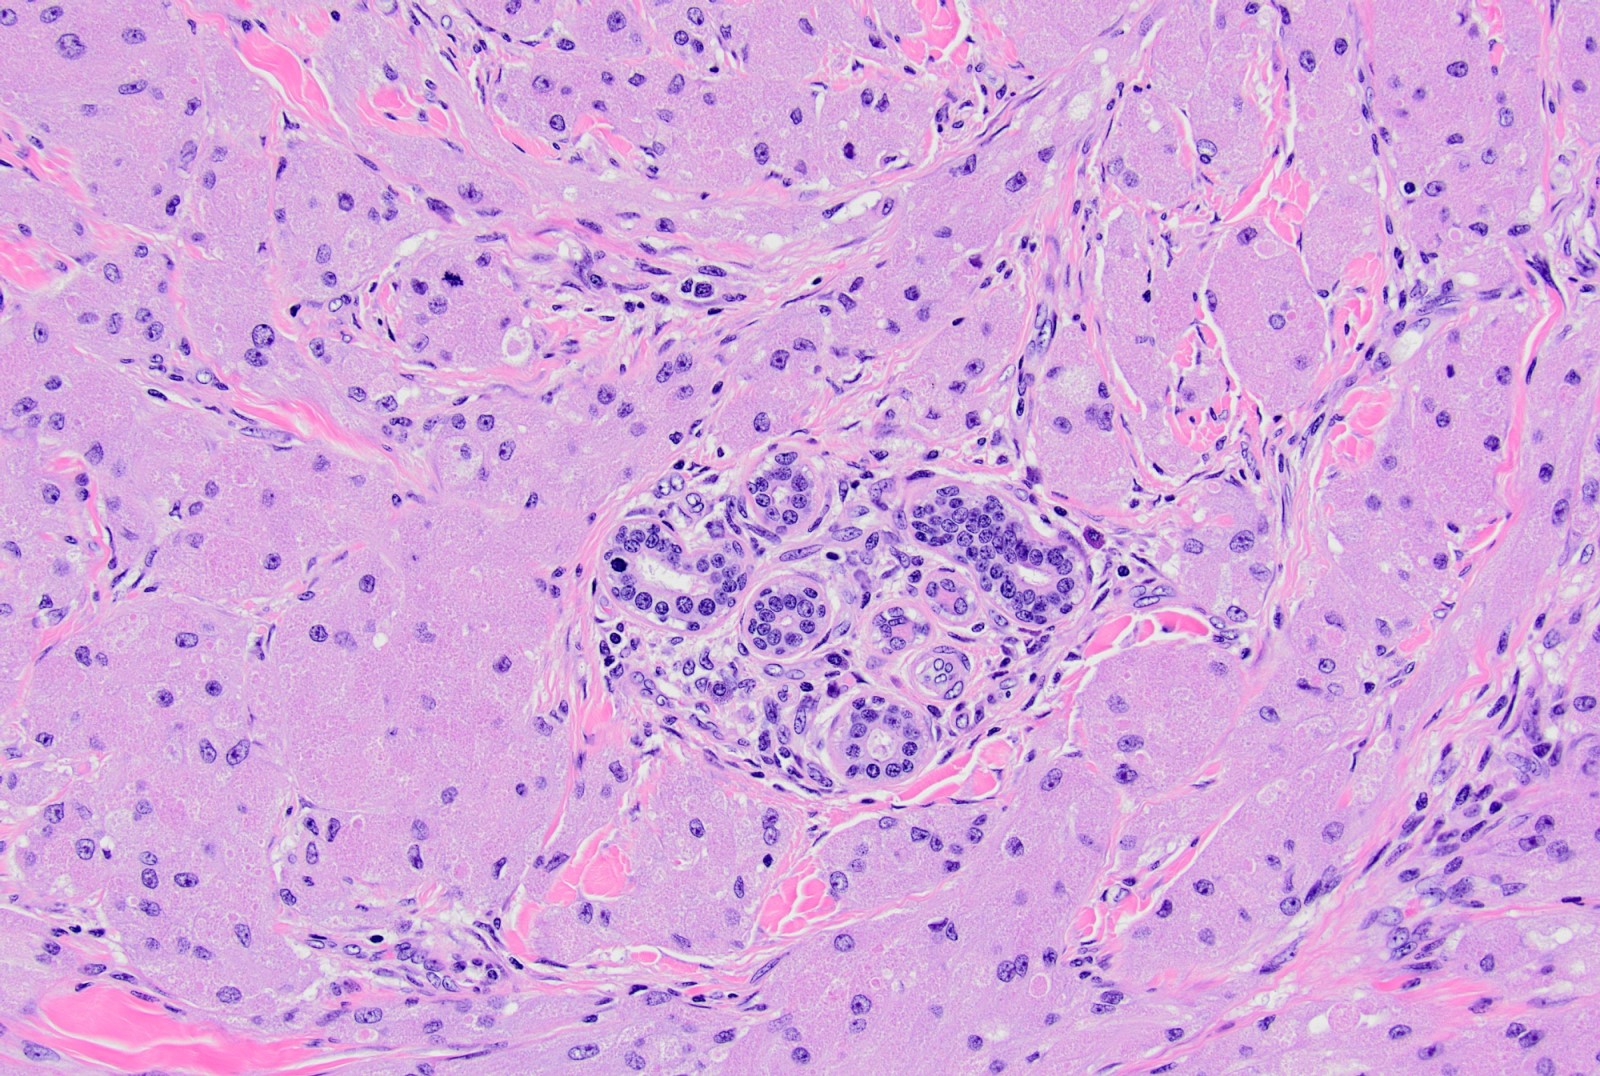
答案
C. 颗粒细胞瘤。颗粒细胞瘤呈 S100 强、弥漫阳性。- A 不正确:乳腺大汗腺化生源于上皮,S100 阴性。
- B 不正确:乳腺上皮 S100 阴性,且图中未显示伴异型的上皮增生。
- D 不正确:浸润性导管癌起源于乳腺上皮,后者 S100 阴性。
相关专题:乳腺颗粒细胞瘤
作者:Salvatore Luceno, M.D., M.Sc.;Anna Biernacka, M.D., Ph.D. · 编辑部最后更新 2026-09-15 · PathologyOutlines 专题
定义 / 概述
- 源自施万细胞的良性神经外胚层肿瘤,由上皮样细胞构成,胞质丰富、呈颗粒状,富含溶酶体。
要点
- 不常见的乳腺肿瘤,具有外周神经鞘(施万细胞)分化。
- 大型上皮样细胞,核形态温和,嗜酸性胞质丰富,富含颗粒(溶酶体)。
- S100 强、弥漫阳性。
- 必须排除其他具有颗粒状形态、侵袭性更强的肿瘤(黑色素瘤、乳腺癌)。
术语
- 颗粒细胞瘤(GCT)。
- WHO 不推荐使用的历史术语:颗粒细胞肌母细胞瘤;Abrikossoff 瘤。
- A.I. Abrikosoff 于 1926 年首次描述,称为肌母细胞性肌瘤(Virchows Arch A Pathol Anat 1926;260:215)。
ICD 编码
- ICD-O:9580/0 — 颗粒细胞瘤,非特指型(NOS)。
- ICD-O:9580/3 — 恶性颗粒细胞瘤。
流行病学
- 可发生于全身各部位;乳腺病例占全部 GCT 的 5–15%(J Surg Oncol 1980;13:301)。
- 相较其他乳腺病变罕见:每 1,000 个乳腺肿瘤中约 1 例;每 100–200 例乳腺癌对应约 1 例(Breast J 2004;10:528)。
- 发生于女性,年龄范围广(19–77 岁)(Arch Pathol Lab Med 2011;135:890)。
- 在非裔美国人中更常见,其发病年龄(平均 41 岁)低于白人美国人(平均 54 岁)(Arch Pathol Lab Med 2011;135:890)。
- 儿童和男性罕见(Clin Imaging 2018;52:334;Autops Case Rep 2019;9:e2019099;BMJ Case Rep 2019;12:e227805;J Ultrasound Med 2011;30:1295)。
- 可偶然与乳腺癌同时出现,或与乳房切除瘢痕相关(Arch Pathol Lab Med 2000;124:709)。
部位
- 最常累及皮肤和皮下组织,也可累及乳腺实质。
- 最常位于内上象限、靠近锁骨上神经;相比之下,乳腺癌最常发生于外上象限。
- 通常单发,但约 18% 的患者有多中心性病变的报道(Breast J 2004;10:528)。
- 偶为双侧。
病理生理
- 似乎源自乳腺小叶间间质中外周神经的施万细胞。
- 多数 GCT(约 60–70%,包括乳腺肿瘤)具有位于 X 染色体的 ATP6AP1 或 ATP6AP2 功能丧失突变,两者互斥;这可能解释女性患病率较高(Nat Commun 2018;9:3533;Genes Chromosomes Cancer 2019;58:373)。
- 这些基因编码调节内体 pH 的液泡 H+-ATPase 组分。
- 囊泡酸化受损和内体分布改变导致胞质内囊泡大量积聚,与组织学形态相对应。
- 确切致癌机制尚未明确。
病因
- 多数病例,包括多灶病例,为散发性。
- 罕见与其他疾病相关,包括 Bannayan-Riley-Ruvalcaba 综合征、1 型神经纤维瘤病、Noonan 综合征和 LEOPARD 综合征(Am J Med Genet A 2003;120A:286;Arch Dermatol 1990;126:1051;Eur J Pediatr Surg 2013;23:257;Clin Genet 2009;75:185)。
临床特征
- 多数患者(约 70%)表现为可触及乳腺肿块,约 25% 因筛查乳腺 X 线异常发现,约 4% 在乳腺恶性肿瘤随访时检出(Surg Oncol 2011;20:97)。
- 最常为孤立病变;较少在乳腺或其他部位出现多发病变(Breast J 2004;10:528)。
- 查体为不规则、坚实肿块,可牵拉皮肤、造成乳头内陷或粘连胸壁,类似乳腺癌(BMJ Case Rep 2013;2013:bcr2012008178)。
- 通常无痛;累及皮肤时可疼痛。
- 皮肤病变质硬,呈肉色至红色。
- 有 GCT 与浸润性乳腺癌同一部位共存的报道(Arch Pathol Lab Med 2002;126:731;Case Rep Oncol 2021;14:303)。
诊断
- 临床和影像表现与乳腺癌相似,需组织诊断(BMJ Case Rep 2024;17:e258326;Cureus 2024;16:e57500;World J Clin Cases 2023;11:8044;Cureus 2024;16:e56774)。
- 通常通过影像引导下空心针穿刺活检诊断,偶用细针穿刺。
- 对具有丰富泡沫状、透明或颗粒状胞质的肿瘤,应考虑 GCT。
- 通常以免疫组化支持诊断;一般建议切除。
影像描述
- 乳腺 X 线表现通常提示恶性可能。常见不规则、毛刺状、星芒状、等密度(有时伴低密度边缘)、不均质,边界清晰程度不一,可伴卷须状延伸 / 促结缔组织增生。
- 偶有皮肤增厚、局部侵犯及与胸大肌相连;通常无钙化。
- 超声表现通常也提示恶性可能:常为实性、不均质、边界不清的肿块,纵横比较高。
- 可见丰富血流,尤其在周边,但并非恒定表现。
- 低回声,伴后方声影,内部回声粗糙,边界回声高。
- MRI / 动态磁共振乳腺成像可能有助于判断病变范围、侵袭性特征及对侧筛查;但尚无明确特异性表现,影像可类似乳腺恶性肿瘤。
- FDG PET:无葡萄糖代谢增高,与良性病变相符。
- 参考文献:Surg Oncol 2011;20:97;Radiol Bras 2020;53:105;J Korean Soc Radiol 2022;83:1195;Medicine (Baltimore) 2020;99:e23264;Br J Radiol 2007;80:970;J Nucl Med 1998;39:1398。
影像图
原文数字乳腺 X 线 / 超声及 MRI 图托管于其他服务器;本站未收录。
预后因素
- 多数为良性(约 99%),生长缓慢。
- 因建议切除,未切除 GCT 的自然病程不明。
- 即使切缘阳性,局部复发风险也很低(Arch Pathol Lab Med 2011;135:890)。
- 极少数 GCT 可表现恶性行为(1–2%)(Am J Surg Pathol 1998;22:779)。
- 罕见恶性类型可转移至腋窝淋巴结,并远处播散至肺、肝或骨(J Ultrasound Med 2011;30:1295)。
病例报告
- 3 岁女孩,乳腺 GCT(Autops Case Rep 2019;9:e2019099)。
- 45 岁女性,乳腺 GCT(Indian J Surg Oncol 2020;11:321)。
- 50 岁女性和 62 岁男性,GCT 均类似乳腺癌(Cureus 2024;16:e57500)。
- 58 岁女性,GCT(Indian J Surg Oncol 2015;6:446)。
治疗
- 局部切除(Surg Oncol 2011;20:97)。
- 不完整切除后,局部复发报道罕见。
临床图像
原文“无痛、颜色改变的病变”和“溃疡性、疼痛性病变”图托管于其他服务器;本站未收录。
大体描述
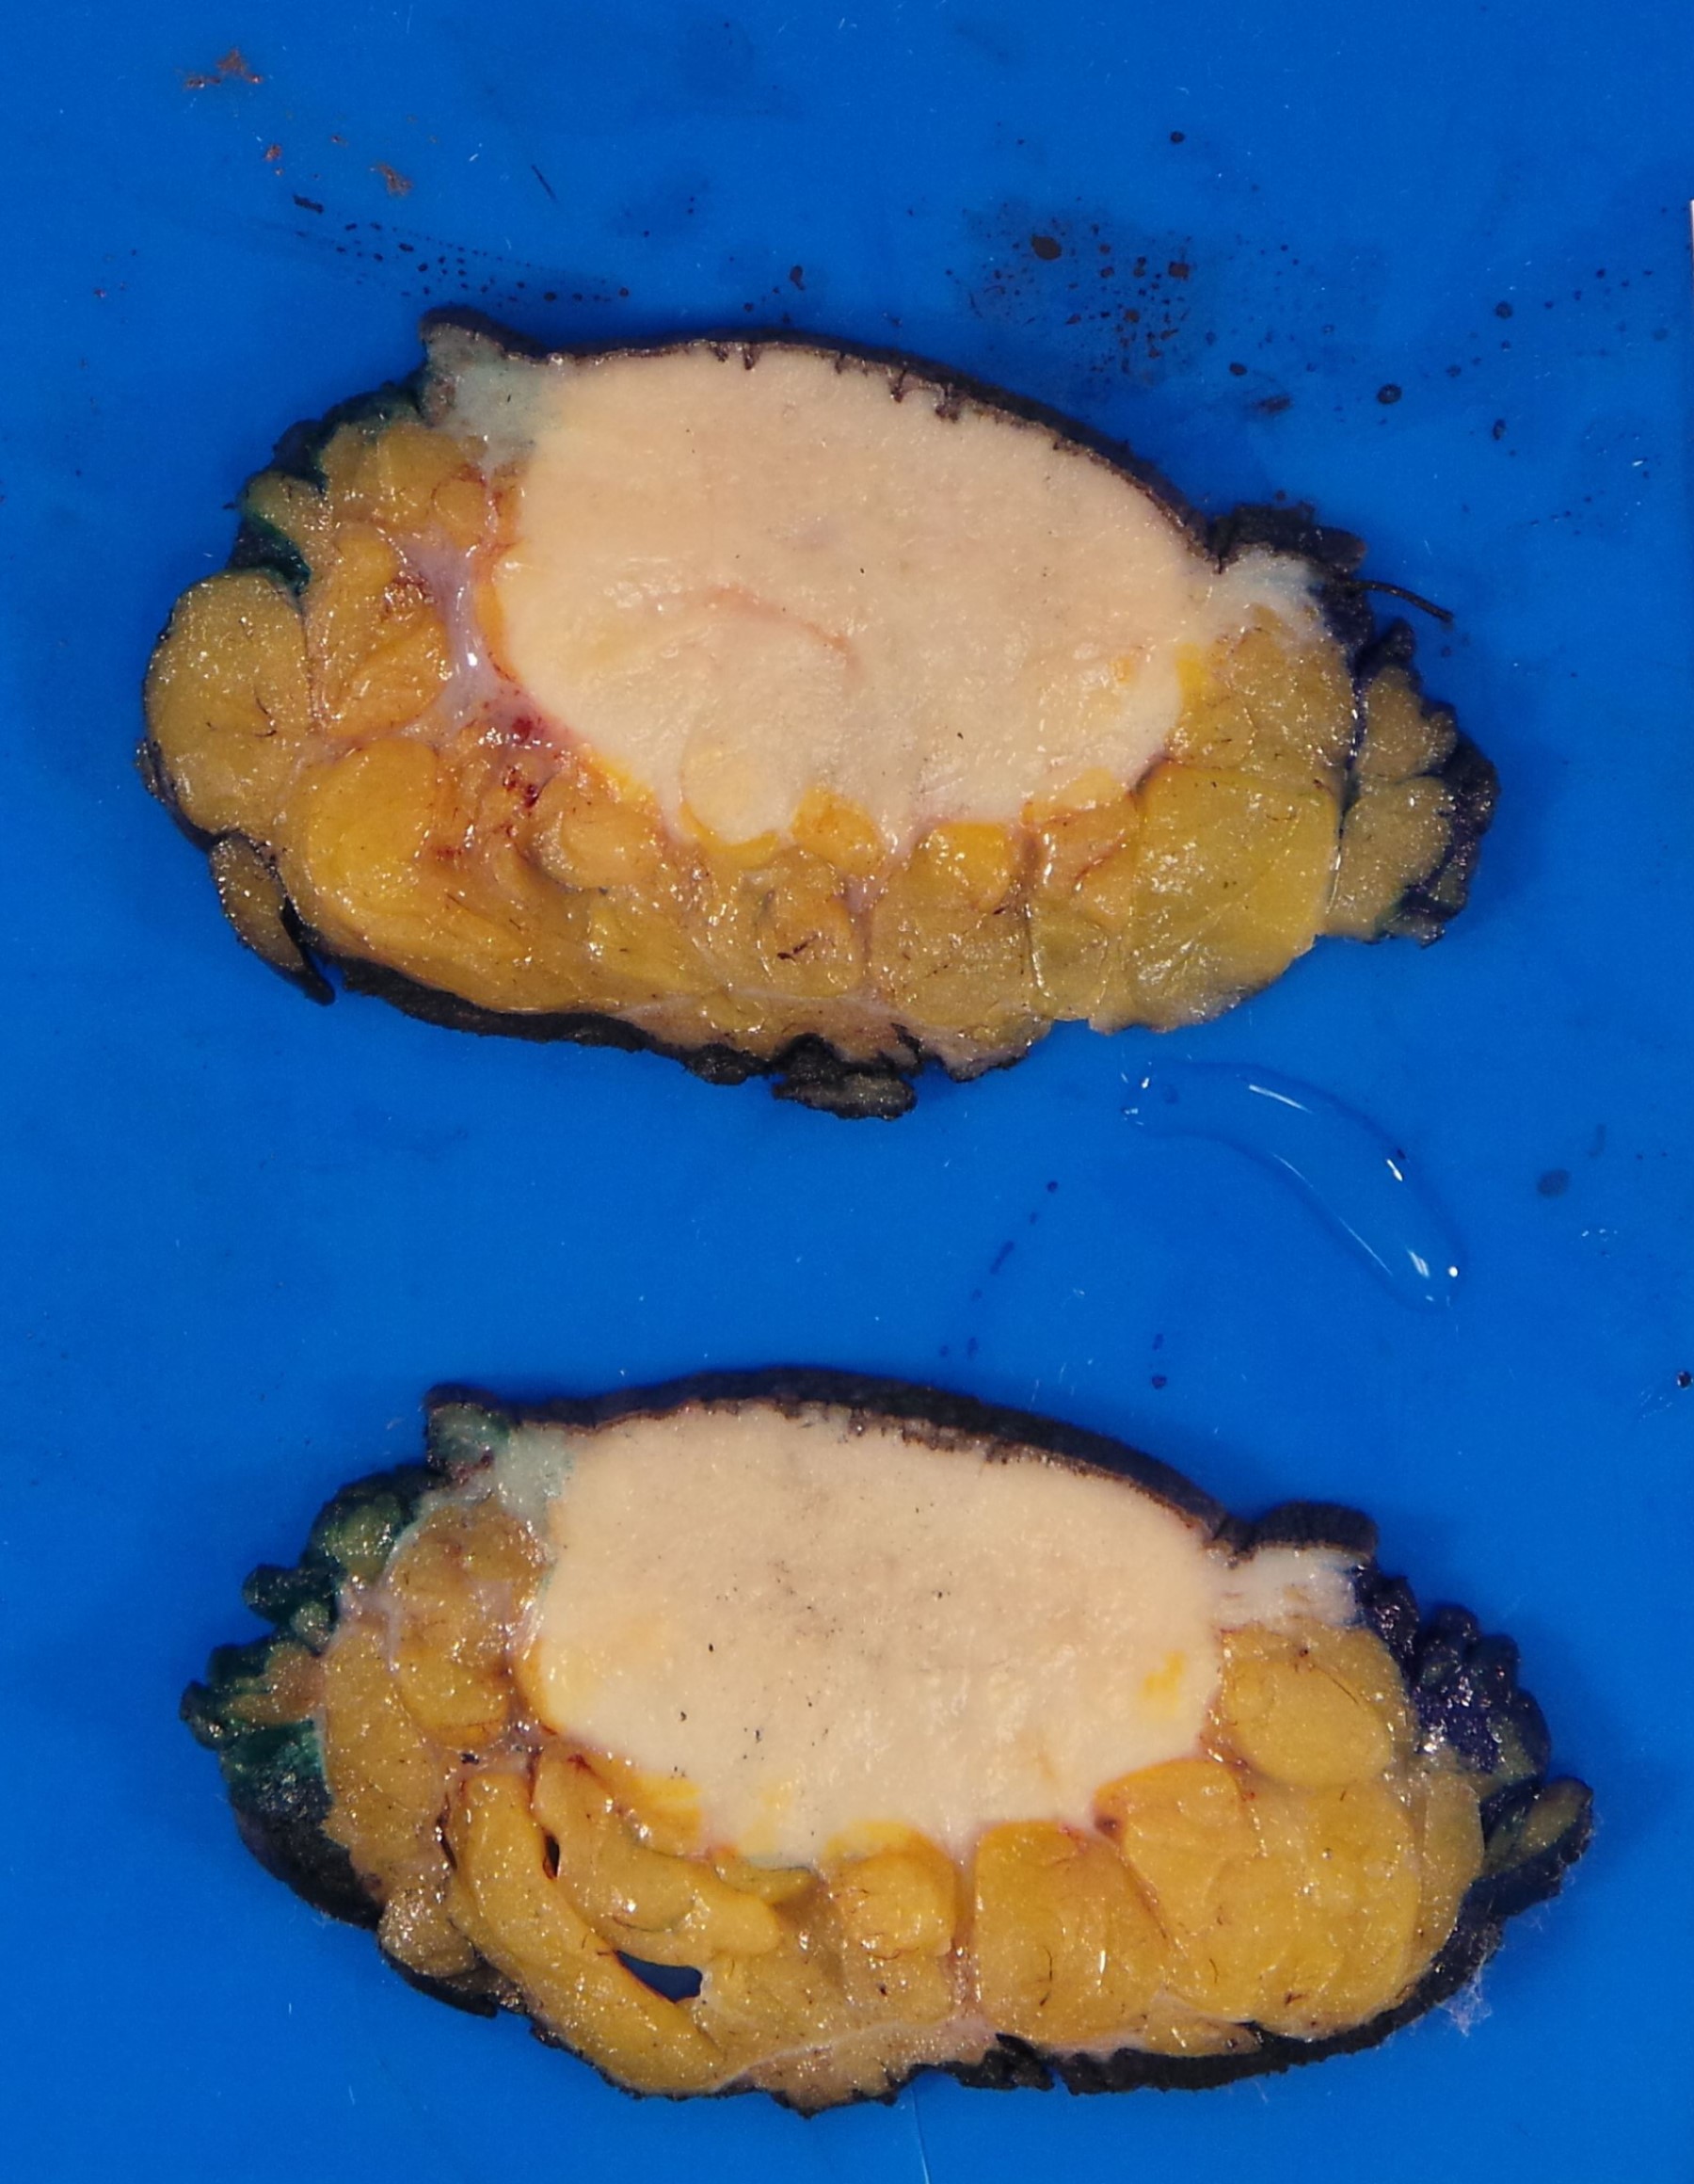
- 实性、均质、棕白色肿块,质韧至硬(Breast J 2004;10:528;Breast J 2000;6:27)。
- 边界可清楚、局限,或不清楚、呈浸润性。
- 通常 1–3 cm,可达 5 cm。
大体图像

镜下(组织学)描述
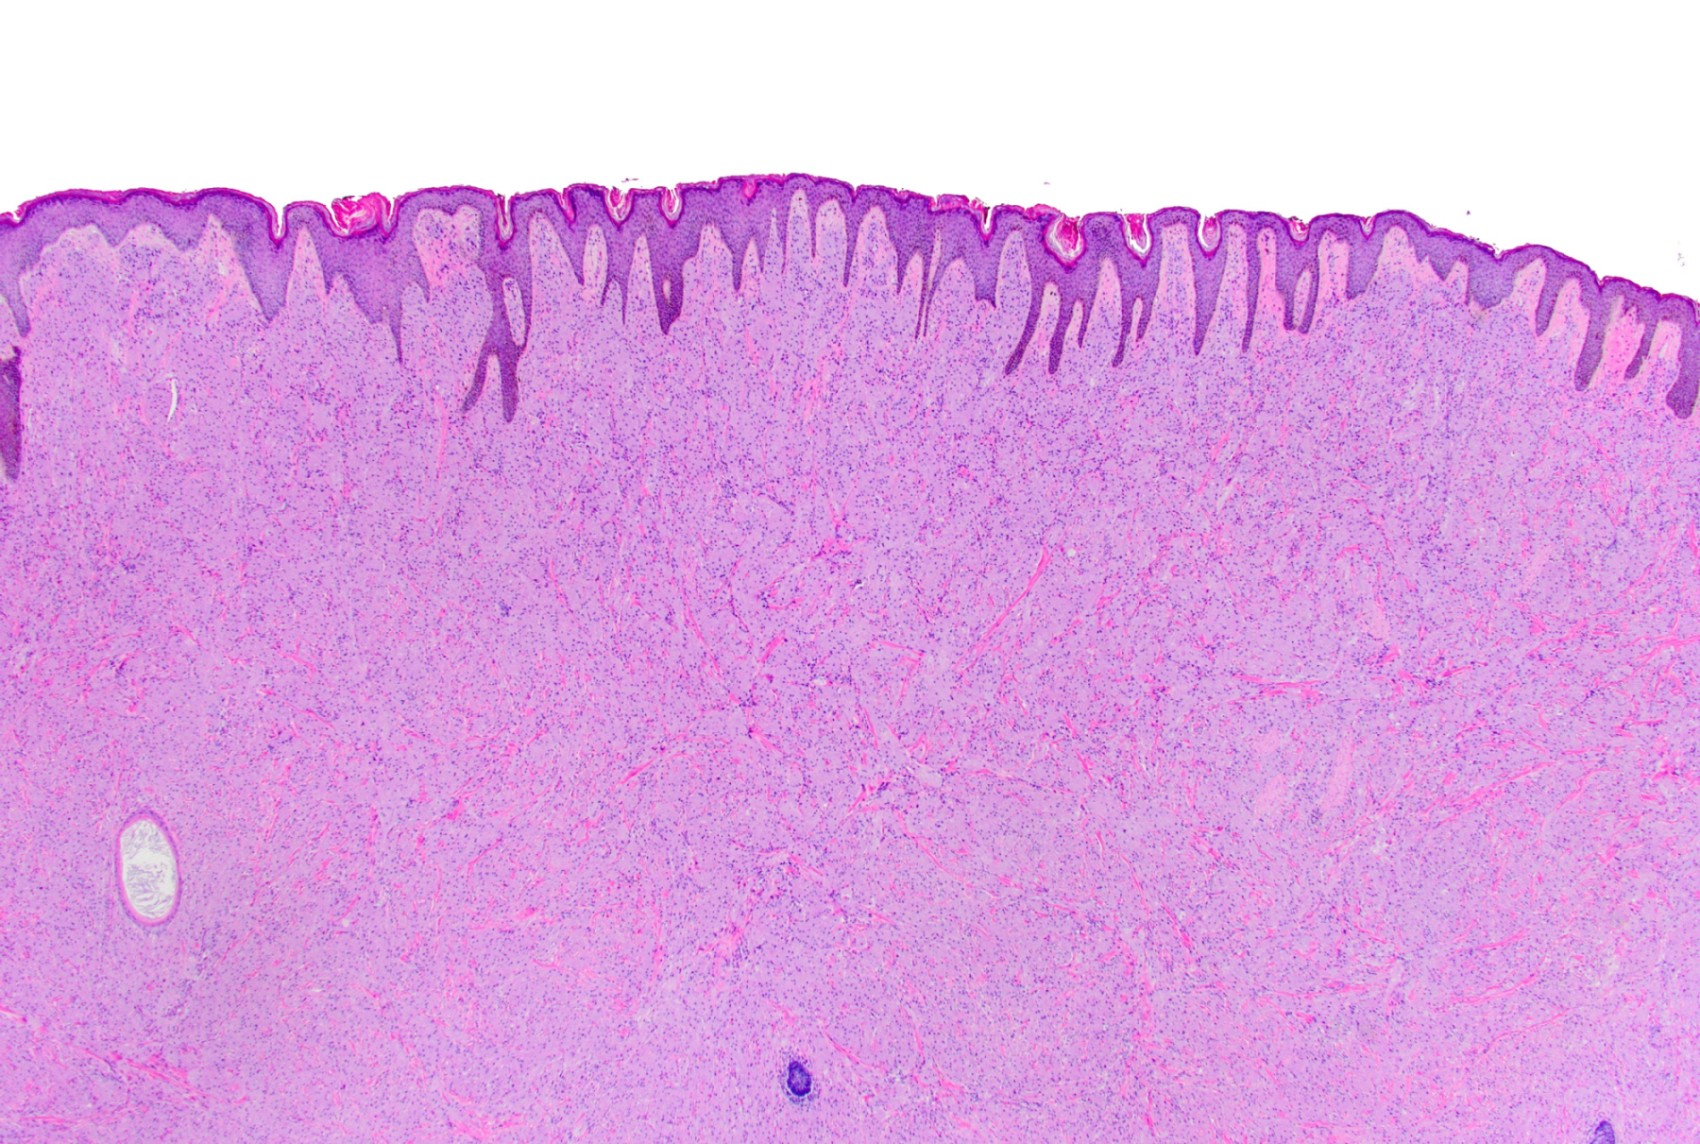
- 分界清楚但无包膜,边缘可局限或呈浸润性。
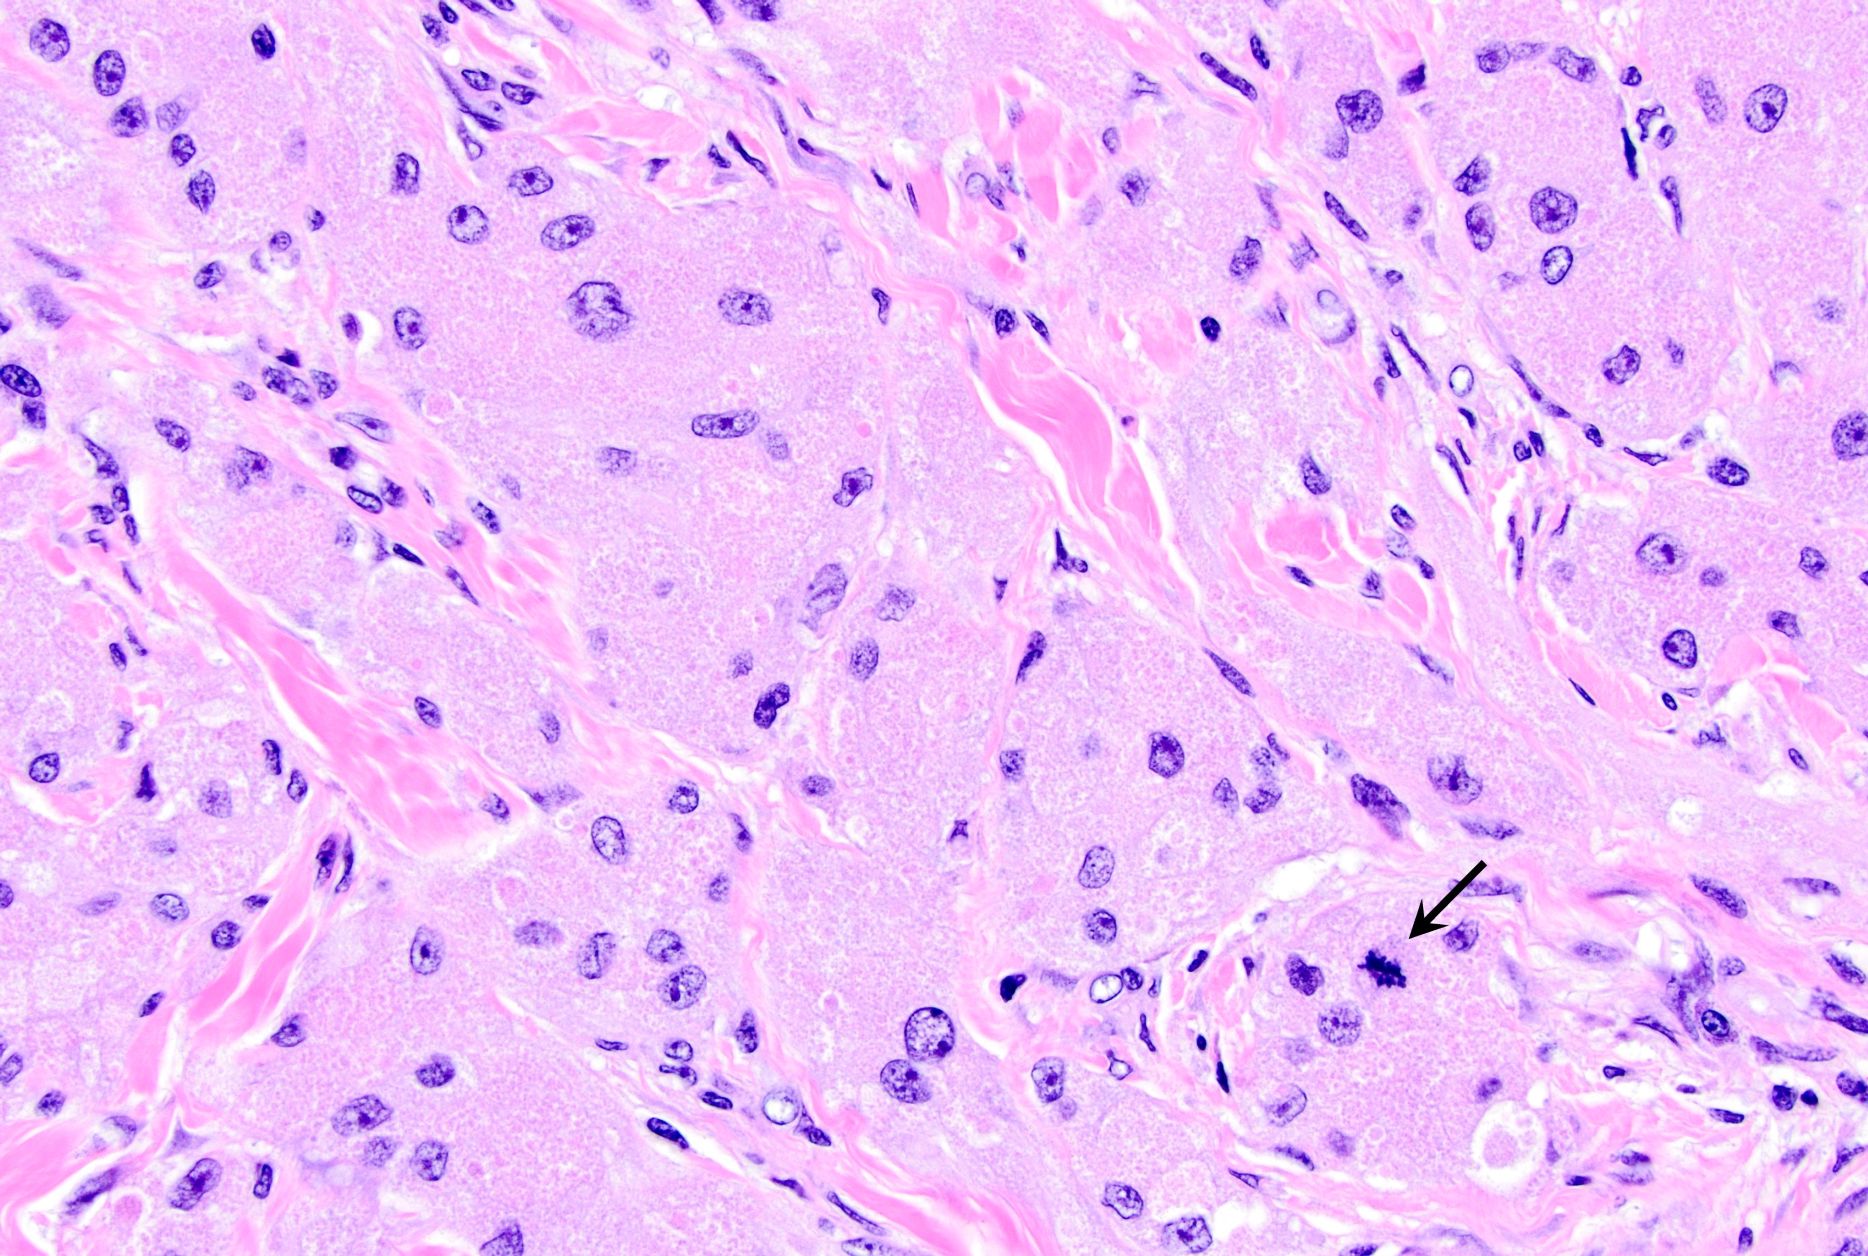
- 细胞呈黏聚性片状、簇状、束状和梁状排列,构成实性增殖。
- 以小巢浸润邻近组织,单细胞浸润较少见。
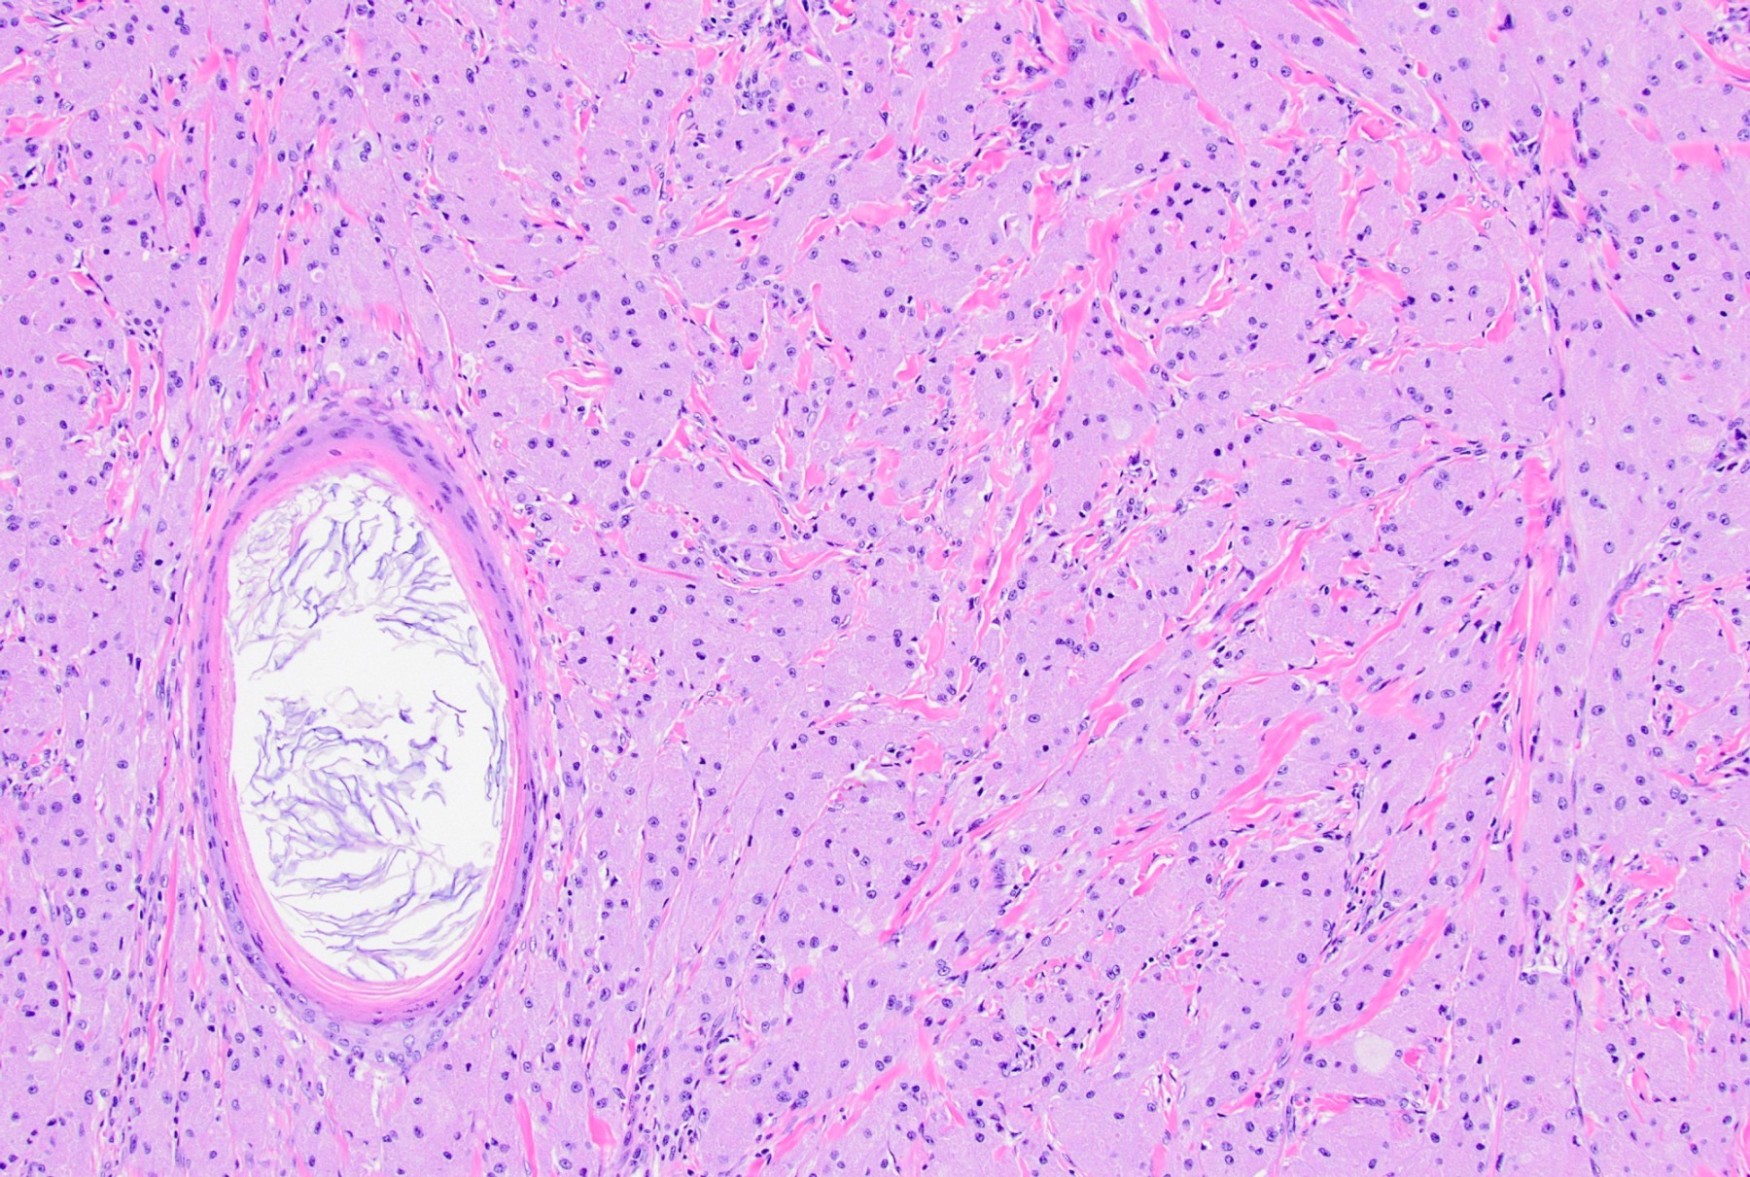
- 细胞大,圆形至多角形,也可呈梭形。
- 细胞边界可不清,呈合体样外观,也可界限清楚。
- 胞质丰富、嗜酸性,因溶酶体积聚而呈细颗粒状;较小溶酶体嗜酸性,较大者周围有晕(Milian 脓疱卵圆小体),PAS 阳性且耐淀粉酶消化。
- 部分肿瘤胞质透明、空泡状。
- 核居中、小而均一、深染,罕呈空泡状;核仁可不明显或明显。
- 核分裂象罕见(Surg Oncol 2011;20:97)。局灶核多形性或偶见核分裂不应被视为恶性证据。
- 间质可为致密胶原性 / 玻璃样变性 / 纤维性,可含分支状薄壁血管、小神经束和数量不等的淋巴细胞、浆细胞。
- 常累及神经周围和血管周围(J Clin Pathol 2014;67:19)。
- 覆盖上皮可出现假上皮瘤样增生,类似鳞状细胞癌(J Surg Oncol 1980;13:301)。
- 恶性 GCT 极罕见(1–2%),按一组组织学标准识别:坏死;梭形细胞形态;空泡状核伴明显核仁;核分裂活性增高(200 倍下每 10 个高倍视野 >2 个核分裂象);高核质比;显著核多形性(Am J Surg Pathol 1998;22:779)。
- 上述 6 项中具备 2 项归为非典型,具备 3 项及以上归为恶性(Breast J 2004;10:528;Arch Pathol Lab Med 2004;128:771)。
- 大体积(>5 cm)也提示需警惕恶性。
- 转移仍是唯一明确无疑的恶性征象(Virchows Arch 2016;468:527)。
镜下(组织学)图像
细胞学描述
- 穿刺物细胞丰富,含黏聚性细胞群和单个细胞,混有结缔组织碎片(Breast J 2000;6:27;Diagn Cytopathol 2007;35:725;Surg Today 2004;34:760;Cytojournal 2014;11:28)。
- 细胞簇可呈合体样,完整单个细胞为多角形。
- 胞质丰富、颗粒状,边界不清。
- 核小,形态温和,染色质细颗粒状,偶有小核仁;可见裸核。
- 细胞膜纤细、脆弱;细胞破裂使颗粒释放到背景中。
- 颗粒在 Romanowsky 染色中为蓝色,在巴氏染色中为红色。
- 无核分裂象、无坏死。
- 鉴别包括癌(尤其大汗腺癌)和黄色肉芽肿性炎症病变。
细胞学图像
原文含“丰富而纤细的胞质”“颗粒状背景和裸核”“类似组织细胞”“核特征”及外部托管的“核与胞质特征”图;本站未收录。
阳性染色
- S100(>95% 病例),核和胞质强、弥漫阳性。
- SOX10(>90%)。
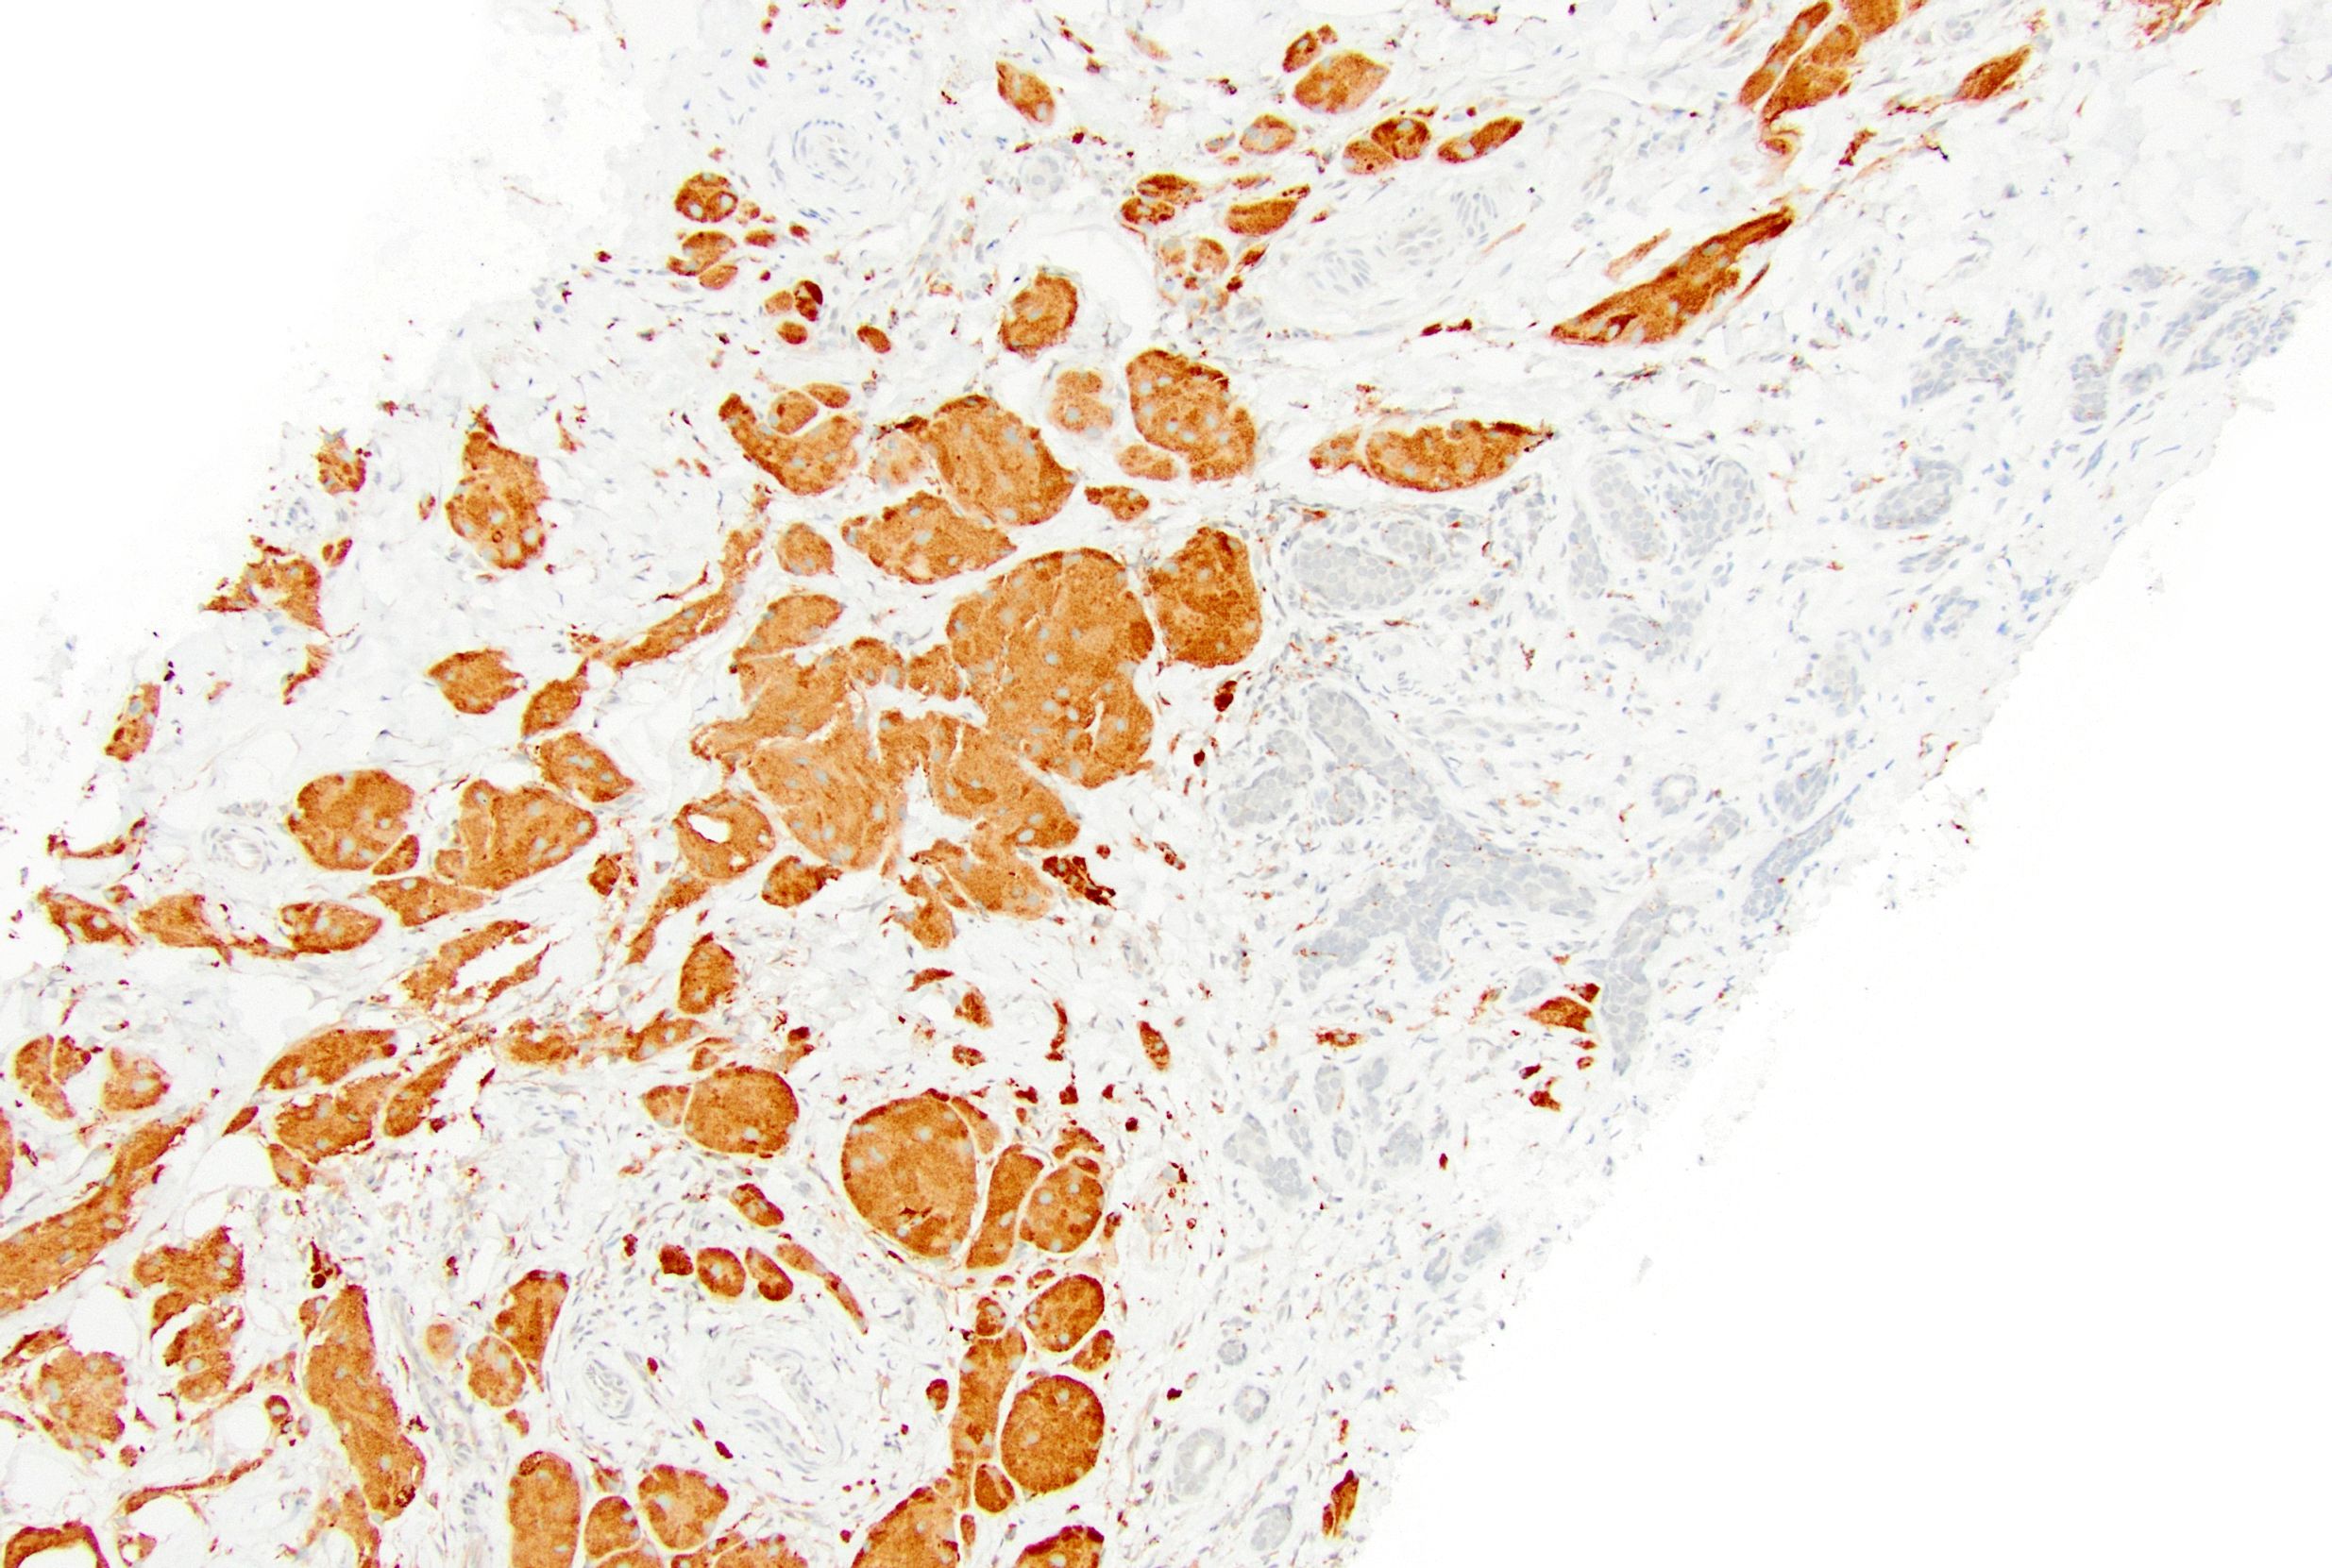
- CD68(>95%)、CD63(NKI-C3):胞质内吞噬溶酶体的非特异性免疫反应。
- 钙视网膜蛋白(calretinin,约 80%)。
- 抑制素-α(约 50%)。
- 神经元特异性烯醇化酶(约 90%)。
- CD56。
- PAS(耐淀粉酶消化)。
- TFE3 和 MITF 强核阳性(Hum Pathol 2015;46:1242;Am J Dermatopathol 2007;29:22)。
- CEA 和波形蛋白局灶阳性。
电镜描述
- 髓鞘样结构、溶酶体。
分子 / 细胞遗传学描述
- 突变负荷低。
- ATP6AP1 和 ATP6AP2 基因功能丧失突变常见。
病理报告示例
- 乳腺,肿块切除:颗粒细胞瘤(2 cm),完整切除(见评注)。
- 评注:切片显示片状排列的多角形细胞,胞质丰富、嗜酸性,核圆,核仁不明显;未见核分裂象或异型。S100 强、弥漫阳性,AE1 / AE3 阴性。
鉴别诊断
- 浸润性乳腺癌,尤其大汗腺型、组织细胞样型:角蛋白阳性。
- 分泌性癌:GATA3、MUC4 阳性。
- 含组织细胞的良性炎症病变(如肉芽肿性乳腺炎、破裂囊肿、脂肪坏死、乳房植入物破裂和硅胶相关病变):组织细胞胞质泡沫状或空泡状,炎细胞浸润增多,可见肉芽肿和巨细胞;需了解临床病史。
- 转移性肿瘤,如肾细胞癌和黑色素瘤:肾细胞癌 PAX8 阳性;黑色素瘤 MelanA、HMB45 阳性。
- 腺泡状软组织肉瘤:圆形至多角形大细胞,边界清楚,染色质空泡状并有明显核仁;呈器官样、巢状生长,具有特征性假腺泡样结构。
练习题 1 及答案
本专题练习题 1 即上方 Image Quiz #195;题干、A–D 选项及答案解析见本文开头。
练习题 2
一名 45 岁患者,2.3 cm 乳腺肿块活检后诊断为颗粒细胞瘤。下列哪种免疫表型最支持该诊断?
- CK7−,ER+
- S100−,ER+
- S100+,CK7−
- S100+,CK7+
练习题 2 答案
C. S100+,CK7−。颗粒细胞瘤 S100 阳性,细胞角蛋白(包括 CK7)阴性。A 不正确,因为颗粒细胞瘤 ER 阴性。B 不正确,因为颗粒细胞瘤 S100 阳性。D 不正确,因为颗粒细胞瘤 CK7 阴性。A 45 year old patient had a 1.5 cm poorly defined breast mass without calcifications on imaging. Tissue sampling was performed and the H&E stained section is shown in the image above. The lesional cells show strong diffuse staining with S100. Which of the following is the best diagnosis?
Select an answer:
- Apocrine metaplasia
- Atypical ductal hyperplasia
- Granular cell tumor
- Invasive ductal carcinoma
Answer
C. Granular cell tumor. Granular cell tumors show strong diffuse S100 positivity.- A is incorrect: apocrine metaplasia of the breast is S100 negative, as they are of epithelial origin.
- B is incorrect: breast epithelium is S100 negative and the image does not show hyperplastic epithelium with atypia.
- D is incorrect: invasive ductal carcinoma originates in the breast epithelium, which is S100 negative.
Related topic: Granular cell tumor of the breast
Authors: Salvatore Luceno, M.D., M.Sc.; Anna Biernacka, M.D., Ph.D. · Last staff update: 15 September 2026 · PathologyOutlines topic
Definition / general
- Benign neuroectodermal tumor derived from Schwann cells and composed of epithelioid cells with abundant lysosome rich granular cytoplasm
Essential features
- Uncommon breast tumor with peripheral nerve sheath (Schwannian) differentiation
- Large epithelioid cells with bland nuclear features and abundant eosinophilic cytoplasm rich in granules (lysosomes)
- S100 is strongly and diffusely positive
- Must exclude other more aggressive neoplasms with granular appearance (melanoma, breast carcinoma)
Terminology
- Granular cell tumor (GCT)
- Historical terminology not recommended by the WHO
- Granular cell myoblastoma
- Abrikossoff tumor
- First described by A.I. Abrikosoff in 1926 as myoblastic myoma (Virchows Arch A Pathol Anat 1926;260:215)
ICD coding
Epidemiology
- Can occur anywhere in the body; breast accounts for 5 - 15% of all GCTs (J Surg Oncol 1980;13:301)
- Rare compared to other breast lesions: 1 per 1,000 breast tumors; 1 per 100 - 200 breast carcinomas (Breast J 2004;10:528)
- Women, wide age range (19 - 77 years) (Arch Pathol Lab Med 2011;135:890)
- More common in African Americans, in whom it occurs at a younger age (mean: 41 years) than in White Americans (mean age: 54 years) (Arch Pathol Lab Med 2011;135:890)
- Children and men are rarely affected (Clin Imaging 2018;52:334, Autops Case Rep 2019;9:e2019099, BMJ Case Rep 2019;12:e227805, J Ultrasound Med 2011;30:1295)
- May present with coincidental breast carcinoma or be associated with mastectomy scars (Arch Pathol Lab Med 2000;124:709)
Sites
- Skin and subcutaneous involvement is the most common
- Breast parenchyma can also be involved
- Most common in the upper inner quadrant near the supraclavicular nerve (in contrast, breast carcinomas are most common in the upper outer quadrant)
- Usually single but multicentricity has been reported in ~18% of patients (Breast J 2004;10:528)
- Occasionally bilateral
Pathophysiology
- Appears to derive from Schwann cells of peripheral nerves in the interlobular breast stroma
- Majority of GCTs (~60 - 70%, including breast tumors) harbor loss of function mutations in the ATP6AP1 and ATP6AP2 genes (mutually exclusive) located on the X chromosome, which may explain the higher prevalence in women (Nat Commun 2018;9:3533, Genes Chromosomes Cancer 2019;58:373)
- Encode vacuolar H+-ATPase components that regulate endosomal pH
- Impaired vesicular acidification and altered distribution of endosomes lead to massive accumulation of intracytoplasmic vesicles (correlating with histologic appearance)
- Exact oncogenic mechanism is not yet understood
Etiology
- Most cases, including multifocal, are sporadic
- Rare association with other conditions, including Bannayan-Riley-Ruvalcaba syndrome, neurofibromatosis type 1, Noonan syndrome and LEOPARD syndrome (Am J Med Genet A 2003;120A:286, Arch Dermatol 1990;126:1051, Eur J Pediatr Surg 2013;23:257, Clin Genet 2009;75:185)
Clinical features
- Majority of patients (~70%) present with a palpable breast lump and ~25% with an abnormality on a screening mammogram; ~4% detected on follow up of breast malignancy (Surg Oncol 2011;20:97)
- Most commonly, it is a solitary lesion; less commonly, multiple lesions are present in the breast or elsewhere (Breast J 2004;10:528)
- On clinical exam, there is an irregular and firm mass, which may retract skin, cause nipple inversion or adhere to the chest wall; it can mimic carcinoma (BMJ Case Rep 2013;2013:bcr2012008178)
- Usually painless; may be painful when it involves skin
- Lesions in the skin are indurated and flesh colored to red
- Colocalization of GCT and invasive breast carcinoma has been reported (Arch Pathol Lab Med 2002;126:731, Case Rep Oncol 2021;14:303)
Diagnosis
- Similar clinical and radiological features to breast carcinomas necessitate tissue diagnosis (BMJ Case Rep 2024;17:e258326, Cureus 2024;16:e57500, World J Clin Cases 2023;11:8044, Cureus 2024;16:e56774)
- Usually made by imaging guided core biopsy, occasionally fine needle aspiration
- GCT should be considered for neoplasms with abundant foamy, clear or granular cytoplasm
- Immunohistochemical studies are typically performed to support the diagnosis
- Excision is generally recommended
Radiology description
- Features on mammography
- Generally infer a suspicion of malignancy
- Common features include irregularity, spiculation, stellation, isodensity sometimes associated with hypodense rims, heterogenicity, variable circumscription and association with tendril-like extensions / desmoplasia
- Occasional skin thickening, local invasion and association with the pectoralis muscle
- Calcifications are usually absent
- Features on ultrasound
- Generally infer a suspicion of malignancy
- Common features include solid, heterogeneous, poorly defined masses with a high depth:width ratio
- Hypervascular echotexture, particularly peripherally, although this is not consistent
- Hypoechoic and display posterior shadowing with a coarse internal echo and high boundary echo
- Magnetic resonance imaging (MRI) / dynamic MR mammography may be useful in determining the extent of disease, the presence of aggressive features and contralateral screening; however, no specific features have been outlined and findings may mimic breast malignancy
- FDG PET: lack of increased glucose metabolism in keeping with a benign lesion
- References: Surg Oncol 2011;20:97, Radiol Bras 2020;53:105, J Korean Soc Radiol 2022;83:1195, Medicine (Baltimore) 2020;99:e23264, Br J Radiol 2007;80:970, J Nucl Med 1998;39:1398
Radiology images
Digital mammography / ultrasound and MRI images from the original topic were hosted on other servers and were not archived locally.
Prognostic factors
- Most are benign (~99% of cases), with a low growth rate
- Since excision is recommended, the natural history of GCT that is not excised is unknown
- There is minimal risk of local recurrence, even when excised with positive margins (Arch Pathol Lab Med 2011;135:890)
- Exceptionally, GCT can show malignant behavior (in 1 - 2% of cases) (Am J Surg Pathol 1998;22:779)
- Rare malignant form can give rise to metastasis to axillary lymph nodes and distant dissemination (lung, liver or bone) (J Ultrasound Med 2011;30:1295)
Case reports
- 3 year old girl with GCT of the breast (Autops Case Rep 2019;9:e2019099)
- 45 year old woman with GCT of the breast (Indian J Surg Oncol 2020;11:321)
- 50 year old woman and 62 year old man both with GCT mimicking breast carcinoma (Cureus 2024;16:e57500)
- 58 year old woman with GCT (Indian J Surg Oncol 2015;6:446)
Treatment
- Treatment is local excision (Surg Oncol 2011;20:97)
- Local recurrence is rarely reported with incomplete excision
Clinical images
Clinical images from the original topic were hosted on other servers and were not archived locally.
Gross description
- Solid, homogeneous, tan-white and firm to hard mass (Breast J 2004;10:528, Breast J 2000;6:27)
- Borders can be well defined, circumscribed or ill defined, infiltrative
- Usually 1 - 3 cm, up to 5 cm
Gross images
Microscopic (histologic) description
- Well demarcated but not encapsulated with a circumscribed or infiltrative border
- Cells arranged in cohesive sheets, clusters, fascicles and trabeculae form solid proliferation
- Infiltration into adjacent tissue in small nests; single cell infiltration is less common
- Cells are large, round to polygonal but may be spindle shaped
- Cell borders are indistinct with syncytial appearance or are well defined
- Cytoplasm is abundant, eosinophilic and finely granular due to the accumulation of lysosomes
- Smaller lysosomes are eosinophilic
- Larger lysosomes have surrounding halo (pustulo-ovoid bodies of Milian)
- PAS positive / diastase resistant
- In some tumors, cytoplasm appears clear and vacuolated
- Nuclei are centrally located, small, uniform and hyperchromatic, rarely vesicular
- Nucleoli may be inconspicuous or prominent
- Mitotic figures are rare (Surg Oncol 2011;20:97)
- Focal areas of nuclear pleomorphism or occasional mitoses should not be interpreted as evidence of malignancy
- Stroma may be dense collagenous / hyalinized / fibrous, may contain arborizing thin walled blood vessels, small nerve bundles and variable amounts of lymphocytes and plasma cells
- Perineural and perivascular involvement is frequent (J Clin Pathol 2014;67:19)
- Overlying epithelium may show pseudoepitheliomatous hyperplasia that may simulate squamous cell carcinoma (J Surg Oncol 1980;13:301)
- Malignant GCT (exceedingly rare, 1 - 2%) recognized by a set of histologic criteria (Am J Surg Pathol 1998;22:779)
- Necrosis
- Spindle cell morphology
- Vesicular nuclei with prominent nucleoli
- Increased mitotic activity (> 2 mitoses per 10 HPF at 200x magnification)
- High N:C ratio
- Significant nuclear pleomorphism
- Classified as atypical when 2 of 6 criteria are present and as malignant when 3 or more criteria are present (Breast J 2004;10:528, Arch Pathol Lab Med 2004;128:771)
- Large size (> 5 cm) is also of concern for malignancy
- Metastasis remains the only unequivocal sign of malignancy (Virchows Arch 2016;468:527)
Microscopic (histologic) images
Cytology description
- Cellular aspirates with cohesive groups and single cells admixed with fragments of connective tissue (Breast J 2000;6:27, Diagn Cytopathol 2007;35:725, Surg Today 2004;34:760, Cytojournal 2014;11:28)
- Clusters may appear syncytial, while intact single cells have polygonal shapes
- Cytoplasm is abundant and granular with indistinct boundaries
- Nuclei are small and bland with finely granular chromatin and occasional small nucleoli; bare nuclei may be present
- Cell membranes appear delicate and fragile; cell disruption releases granules to the background
- Granules are blue with Romanowsky stains and red with the Papanicolaou stain
- No mitotic figures, no necrosis
- Differential diagnosis includes carcinomas (in particular apocrine) and xanthogranulomatous inflammatory lesions
Cytology images
Cytology images from the original topic were not archived locally.
Positive stains
- S100 (> 95% of cases), strong and diffuse in nuclear and cytoplasmic
- SOX10 (> 90%)
- CD68 (> 95%), CD63 (NKI-C3), nonspecific immunoreactivity in intracytoplasmic phagolysosomes
- Calretinin (~80%)
- Inhibin-α (~50%)
- Neuron specific enolase (~90%)
- CD56
- PAS (diastase resistant)
- Strong nuclear TFE3 and MITF (Hum Pathol 2015;46:1242, Am J Dermatopathol 2007;29:22)
- Focal CEA and vimentin
Electron microscopy description
- Myelin figures, lysosomes
Molecular / cytogenetics description
- These tumors have a low mutation burden
- Frequent loss of function mutations in the ATP6AP1 and ATP6AP2 genes
Sample pathology report
- Breast, lumpectomy:
- Granular cell tumor (2 cm), completely excised (see comment)
- Comment: Sections show sheets of polygonal cells with abundant eosinophilic cytoplasm, round nuclei and inconspicuous nucleoli; no mitosis or atypia are seen. S100 is strongly and diffusely positive, whereas AE1 / AE3 is negative.
Differential diagnosis
- Invasive breast carcinomas, in particular apocrine, histiocytoid: Keratin+
- Secretory carcinoma: GATA3+, MUC4+
- Benign inflammatory lesions containing histiocytes (e.g., granulomatous mastitis, ruptured cysts, fat necrosis, ruptured breast implants and silicone): Histiocytes with foamy or vacuolated cytoplasm, increased inflammatory infiltrate, granulomas, giant cells; Investigate clinical history
- Metastatic tumors (e.g., renal cell carcinoma, melanoma): Renal cell carcinoma:; PAX8+; Melanoma:; MelanA+, HMB45+
- Alveolar soft part sarcoma: Large, round to polygonal cells with well defined cell borders; Vesicular chromatin with a prominent nucleolus; Organoid and nest-like growth pattern with characteristic pseudoalveolar-like structures
Practice question #1 and answer
Practice question #1 for this topic is Image Quiz #195 above; see the stem, choices A–D, and answer explanation at the top of this page.
Practice question #2
A 45 year old patient, status postbiopsy of a 2.3 cm breast mass, was found to have a granular cell tumor. Which of the following immunophenotype profiles best supports this diagnosis?
- CK7-, ER+
- S100-, ER+
- S100+, CK7-
- S100+, CK7+
Practice answer #2
C. S100+, CK7-. Granular cell tumors are positive for S100 and negative for cytokeratins, including CK7. Answer A is incorrect because granular cell tumors are ER-. Answer B is incorrect because granular cell tumors are S100+. Answer D is incorrect because granular cell tumors are CK7-.Cite this page: Luceno S, Biernacka A. Granular cell tumor. PathologyOutlines.com website. https://www.pathologyoutlines.com/topic/breastgct.html. Accessed September 15th, 2026.
English text and images © contributors and PathologyOutlines.com. For personal study only; not medical advice.